A 75 year old woman is an inpatient at 2 days after a successful femoral-popliteal bypass. The surgery was performed because of a significant atheroscerotic peripheral vascular disease causing severely impeded blood flow to her right leg. The patient has been doing well since the completion of her surgery but on the 2nd post operative day she describes a sudden feeling that her heart is beating very fast , which seems like racing. She denies any chest pain, dizziness, or difficulty breathing. She says that she has never experienced a similar feeling before.
Past History: Peripheral vascular disease, Hypertension and mild Coronary artery disease.
Medication: Her medications include ASA, clopidogrel ( started post operatively), metoprolol, and enalapril. Prior to surgery she was taking pentoxifylline.
Patient was a heavy smoker for several years but quit 2 years ago.
On auscultation of her chest there was a rapid heart beat with significant irregularity.
Her H/R was 120 beats/min and BP was 145/83 mmHg.
As ECG was done and following was seen:
Irregular QRS rate with no discernible P waves
Diagnosis : Atrial Fibrillation
Study and Memorize Medical Conditions With The Help Of Photos. Useful Site For Medical Students, Doctors And Nurses.
Wednesday, February 11, 2015
A 55 Year Old Diabetic Patient Presents With End Stage Renal Failure
A 55 year old man who is a known case of diabetes for almost 15 years presents with symptoms of end stage renal failure. His diabetes was mostly uncontrolled and his recent HbA1c level was 10. The patient has also been non compliant with his medicines. On examination the patient had bilateral lower extremity edema, and on laboratory workup he has a massive proteinuria. A biopsy of his kidney was done and following was seen on histopathology:
Glomeruli with Kimmelstiel-Wilson nodules. The smallest nodules can be more cellular and the greatest nodules tend to be acellular in the centre and surrounded by more cellular zones. Capillaries are seen around these nodules, sometimes adopting an aspect in garland (like in the three nodules indicated with arrows); in some cases we see microaneurisms around nodules. Notice the variability of size of the nodules (H&E, X.400).
The patient was diagnosed as a case of End stage Diabetic nephropathy.
Glomeruli with Kimmelstiel-Wilson nodules. The smallest nodules can be more cellular and the greatest nodules tend to be acellular in the centre and surrounded by more cellular zones. Capillaries are seen around these nodules, sometimes adopting an aspect in garland (like in the three nodules indicated with arrows); in some cases we see microaneurisms around nodules. Notice the variability of size of the nodules (H&E, X.400).
The patient was diagnosed as a case of End stage Diabetic nephropathy.
Monday, February 9, 2015
A 54 Year Old Man Presents With A Chronic Heartburn
A 54 year old man presents to his primary care physician with the complains of a chronic heartburn that is not responding to medications. He says that he has intermittent symptoms of heartburn for several years but now over the past year the episodes have been more frequent and occasionally painful. He is taking omeprazole which was helping initially but now it seems that his problem is not getting any better. He describes his heartburn as a burning sensation behind the sternum and is worse after eating spicy food or bending over. He denies any episodes of dysphagia, vomiting, blood in stools etc. On examination the patient is an obese man with a normal findings on all the systems.
A Barium Swallow was done as a part of the workup and following was seen:
Air-contrast esophagram shows thick esophageal mucosal folds (arrows) and an ulcer (arrowhead) due to GERD.
Single contrast esophagram shows stricture (arrow) and sliding hiatus hernia
The patient was diagnosed as a case of Sliding Hiatal hernia with secondary GERD
Case Discussion:
Hiatal Hernia: is the herniation of a section of the stomach above the level of the diaphragm
A Barium Swallow was done as a part of the workup and following was seen:
Air-contrast esophagram shows thick esophageal mucosal folds (arrows) and an ulcer (arrowhead) due to GERD.
Single contrast esophagram shows stricture (arrow) and sliding hiatus hernia
The patient was diagnosed as a case of Sliding Hiatal hernia with secondary GERD
Case Discussion:
Hiatal Hernia: is the herniation of a section of the stomach above the level of the diaphragm
- Sliding Type: Gastroesophageal junction and stomach are displaced above the diaphragm. (most common 95% cases)
- Paraesophageal Type: stomach protrudes through the diaphragm, but the gastroesophageal junction remains fixed in the correct location.
Sunday, February 8, 2015
A 4 Year Old Child Presents With Fever And Rash
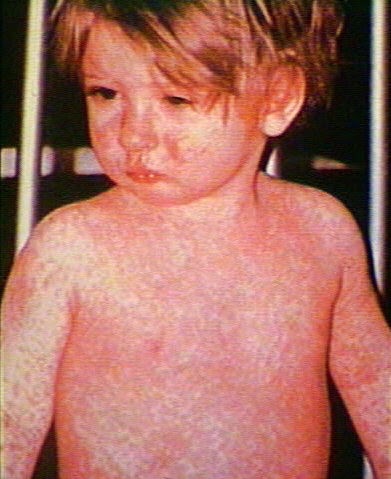
A 4 year old female child is brought to a rural primary care clinic by her mother with the complains of a high grade fever for about a week followed by development of a rash that started on the head and face which has now spread to involve the entire body. Mother describes that the child has been very irritable, has no appetite and refusing to eat , has a runny nose and a hacking cough. The patient has been breathing faster than usual and shows no interest in playing with her toys.
Mother says that the child has never been vaccinated because of their cultural beliefs against vaccinations. The child has normal growth and development for her age.
On Examination Patient has a fever of 102 F , a respiratory rate of 52 breaths per minute and a generalized maculopapular rash covering her entire body. The picture is shown as below;
What is the Diagnosis ?
?
?
.
.
Mother says that the child has never been vaccinated because of their cultural beliefs against vaccinations. The child has normal growth and development for her age.
On Examination Patient has a fever of 102 F , a respiratory rate of 52 breaths per minute and a generalized maculopapular rash covering her entire body. The picture is shown as below;
What is the Diagnosis ?
?
?
.
.
35 Year Old Woman Complaining Of Pain In Her Right Calf
A 35 year old female presents to the hospital with the complains of pain in her right calf that started a few days ago and is now worsening. The pain is constant , 8/10 in intensity, and aggravated on walking and extending the knee. It is associated with swelling and redness of her calf region. The pain is slightly relieved by elevation of her foot and on taking ibuprofen. Patient gives a history of travelling a 15 hour flight 1 week ago. She is on oral contraceptive pills for last 2 years.
On examination the right calf appears red and swollen compared to the left side but there is no ulceration or abnormal pigmentation. On palpation the right calf is warmer compared to the left and there is a positive pitting pedal edema on the right side. The pulses are palpable and felt equal on both sides. Mobility is normal on both sides in the ankle, knee and hip joints. There is a positive Homan's sign on the right side.
The picture of her legs is shown below:
What is the differential diagnosis?
On examination the right calf appears red and swollen compared to the left side but there is no ulceration or abnormal pigmentation. On palpation the right calf is warmer compared to the left and there is a positive pitting pedal edema on the right side. The pulses are palpable and felt equal on both sides. Mobility is normal on both sides in the ankle, knee and hip joints. There is a positive Homan's sign on the right side.
The picture of her legs is shown below:
What is the differential diagnosis?
- Deep vein thrombosis
- Cellulitis
- Myositis
- Rupture of Baker's cyst
- Hematoma
- Spasm due to injury or sprain
What workup is advised in the above described case?
- Doppler Ultrasound
- D-dimer
- Hypercoagulability testing
- CBC with differential
- CPK and myoglobin level
- CT venography
Saturday, February 7, 2015
A 63 Year Old Man Presents With The complains Of Burning Epigastric pain
A 63 year old man presents to his primary care physician with the complaint of burning epigastric pain that occurs soon after eating. He says the pain begins within an hour after taking the meals and also describes having mild nausea associated with the pain. He says that these symptoms have begin about 2 months back and in the last week he had an episode of vomiting and he noticed some brown discoloration in his vomitus. He denies having any blood in the stool or any history of weight loss.
He gets some pain releif by over the counter antacids and ranitidine.
Past History: His past history is significant for osteoarthritis in both his knees and he has been taking naproxen and asprin for the pain relief.
On examination there was mild tenderness on palpation in the epigastric area otherwise no other abnormality was detected.
What is the Differential Diagnosis on the basis of above given history and examination?
Differential Diagnosis:
He gets some pain releif by over the counter antacids and ranitidine.
Past History: His past history is significant for osteoarthritis in both his knees and he has been taking naproxen and asprin for the pain relief.
On examination there was mild tenderness on palpation in the epigastric area otherwise no other abnormality was detected.
What is the Differential Diagnosis on the basis of above given history and examination?
Differential Diagnosis:
- Gastritis
- Peptic ulcer disease
- Zollinger Ellison syndrome
- Pancreatitis
- Gastro esophageal reflux disease
- Gastric cancer
The patient was referred for an esophago-gastro-dudenoscopy and has following picture seen:
An ulcer was seen on the lesser curvature of the stomach.
Diagnosis: Gastric ulcer (peptic ulcer disease) secondary to NSAID overuse.
Subscribe to:
Posts (Atom)